Nearly 60% of patients
struggle with social situations due to difficulty recognizing faces9*
“People would say hi to me, and I’d have no idea who they were.” — Person living with Stargardt disease
*In one study.

Stargardt disease type 1 (STGD1) causes irreversible retinal damage that standard visual acuity exams cannot diagnose.1,2 Yet, due to its low prevalence, it’s not always top of mind as a cause of vision loss.1
Unexplained central vision loss demands more than watch and wait1

Stargardt disease is a progressive inherited retinal disease (IRD) that results in irreversible central vision loss, often progressing to legal blindness (vision of 20/200 or worse).3-5 Stargardt disease is an autosomal recessive genetic condition and the most common form of juvenile macular degeneration.4,6 Although the classic presentation of Stargardt disease involves symptoms presenting in adolescence, clinical onset can occur anytime between childhood and the ninth decade of life.3,7

STGD1 impacts up to59,000 peoplein the US.8
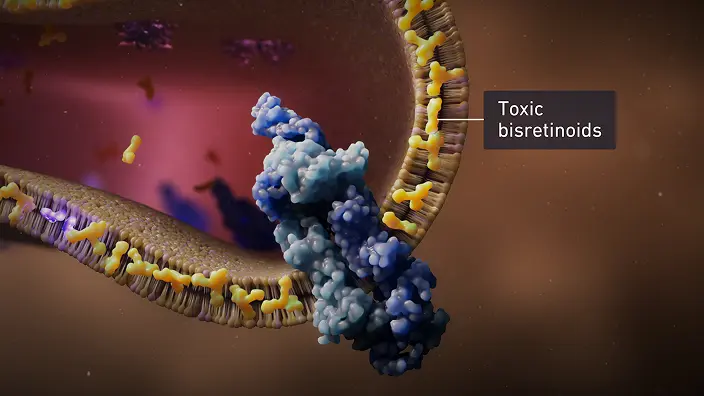
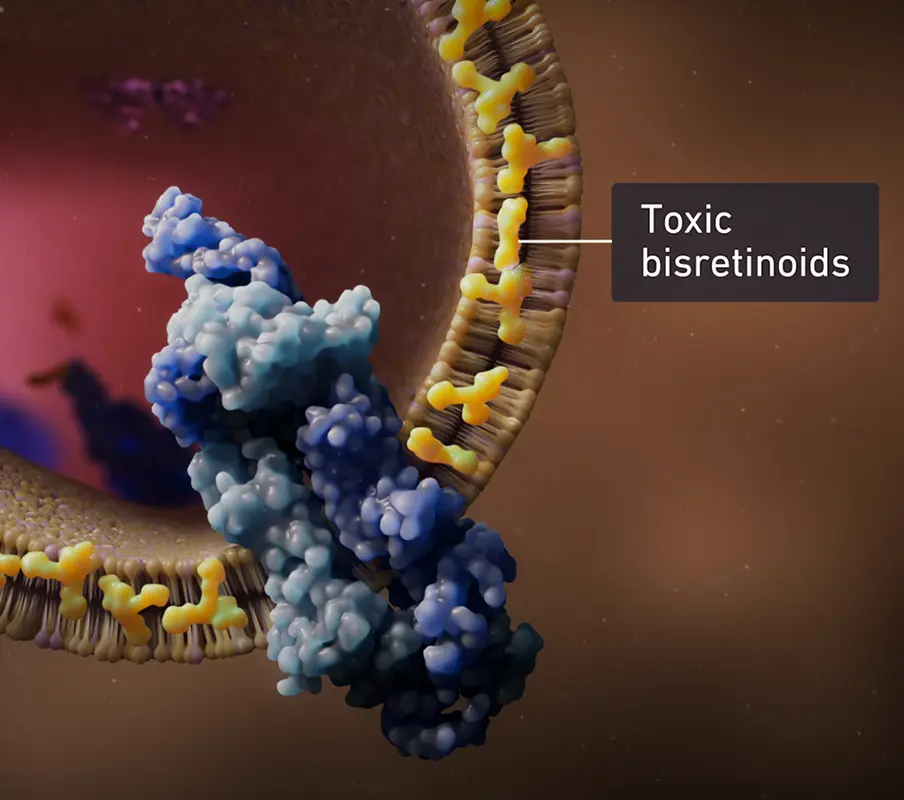
ABCA4 is a transporter protein critical for recycling visual cycle byproducts. Learn more about how ABCA4 protein dysfunction can impact retinal health and vision.3
The most common early symptoms include central vision that is blurry, distorted, or has dark areas. This vision loss cannot be corrected with lenses and often spares peripheral vision. Many patients begin to exhibit symptoms as early as childhood or adolescence, although symptom onset can occur later in adulthood.3,10,11
Other frequent symptoms include:



Worsening vision often manifests as declining participation in sports and leisure activities, challenges with social engagement, or increased frustration with daily tasks. Many patients struggle with daily activities like driving and reading.9
Recognizing these symptoms as early as possible is critical to raise suspicion of Stargardt disease and take timely action toward a confirmed diagnosis.1
Nearly 60% of patients
struggle with social situations due to difficulty recognizing faces9*
“People would say hi to me, and I’d have no idea who they were.” — Person living with Stargardt disease
*In one study.
Patients often endure a lengthy diagnostic journey, as early symptoms can be challenging to identify due to the disease’s rarity and vast clinical variability.1
This prolonged delay means many patients experience irreversible vision loss before receiving a confirmed genetic diagnosis.1
An early Stargardt disease diagnosis ends clinical ambiguity and gives your patients the clarity they need to plan for their future.1

In one study, the diagnostic journey from symptom onset to evaluation by an IRD specialist averaged11 years1
Diagnosing Stargardt disease relies on advanced multimodal imaging and genetic testing.1,4
If you suspect Stargardt disease and lack advanced imaging capabilities. Consider immediately referring to a retina specialist to help confirm a diagnosis.1,4
Help prevent prolonged diagnostic journeys for your patients by referring them to a retina specialist for advanced imaging and genetic testing to confirm a diagnosis. This proactive step establishes a vital baseline for monitoring progression and prepares patients for emerging therapies.1,4

Diagnosing Stargardt disease